
Nonsurgical Body Contouring
An umbrella term for the applications that reshape the body’s outline without incisions or general anaesthesia — reducing localised fat, working on skin texture and supporting muscle tone, each chosen according to what is actually causing the appearance.

What does nonsurgical body contouring mean?
Nonsurgical body contouring is not one device or one procedure. It describes a group of applications that change the shape of a body area without cutting, suction or general anaesthesia. What they share is the route: energy, cold, microinjection or electromagnetic stimulation is delivered from outside the body, and the visible change follows from how the tissue responds over the weeks afterwards.
The starting point is almost always the same complaint — an area that does not respond in proportion to the rest of the body. Understanding why it does not respond is what separates one plan from another, because the outline of the body is produced by several separate layers:
- Subcutaneous fat. The layer between skin and muscle. Its distribution is largely determined by hormones and genetics, which is why some deposits persist at a stable weight.
- Connective tissue. The fibrous bands that run between skin and deeper layers. When these tighten unevenly, the surface dimpling described as cellulite appears — even in people with very little fat.
- Skin quality. Collagen and elastin content determine how well the skin retracts after weight change or pregnancy.
- Muscle. The tone and volume of the muscle beneath give the area its underlying shape; a weak abdominal wall changes the profile regardless of the fat above it.
Two people describing the same problem — “my abdomen doesn’t go down” — can therefore need entirely different approaches. Fat-focused methods will not improve laxity, and muscle stimulation will not remove a fat deposit. Assessment comes before the choice of method.

Which applications fall under this heading?
 Cold LipolysisFat cells are cooled to a temperature the surrounding tissue tolerates, and the body clears them gradually over the following weeks.See how it works →
 Cellulite MesotherapySmall doses of a prepared solution delivered just beneath the skin, where the concern is surface irregularity and circulation rather than volume.See the course →
 Injection LipolysisMicroinjection aimed at small, stubborn fat deposits that are too limited in area for a device applicator to be used.See where it is used →
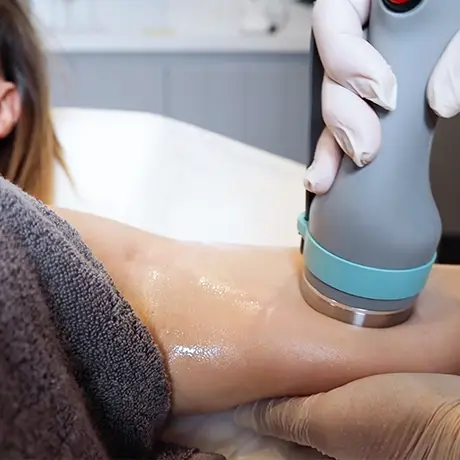 Onda CoolwavesMicrowaves at a frequency absorbed preferentially by fat heat the subcutaneous layer while the skin surface is kept protected.About the technology →
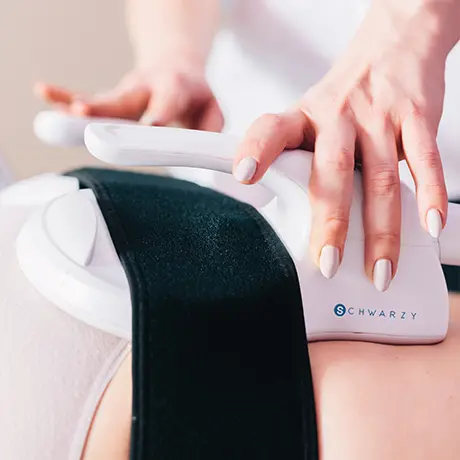 SchwarzyElectromagnetic stimulation produces deep involuntary contractions that voluntary exercise cannot reproduce, used where the underlying issue is muscle tone rather than fat.How it is applied →
In practice a plan often draws on more than one of these, and the order in which they are applied matters as much as the selection.
How the process is planned
Assessment. The area is examined standing and lying down. Fat thickness is checked by pinch, skin retraction is tested, and the tone of the underlying muscle is assessed separately. Weight history is relevant — a stable weight makes results more predictable.
Medical history. Medication, thyroid and metabolic conditions, hernias, clotting disorders, previous surgery in the area and any implanted device are all discussed, because several of these determine which methods are appropriate.
Method and sequence. A single application may be enough, or a staged plan may be preferred — for example, reducing a fat deposit first and reassessing skin laxity once the volume has settled.
Sessions. Most applications in this group take between thirty minutes and an hour and are performed without anaesthesia. Session numbers and intervals differ by method and are set during planning.
Afterwards. Everyday activity usually resumes the same day. Temporary redness, tenderness, mild swelling or numbness in the treated area is common and settles within days.
What it cannot do
None of these applications is a weight-loss treatment. They address the distribution of tissue, not total body weight, and the scale on which they work is the outline of a defined area rather than the whole body. Where the main aim is weight reduction, that is better addressed first — contouring is more predictable at a stable weight.
They also do not remove skin. Where there is significant excess skin — after major weight loss, for instance — the achievable change is limited, and a surgical assessment is the more honest answer. And they do not prevent the remaining fat cells from enlarging again: results are maintained by weight stability, not by the procedure alone.
Who is it not suitable for?
- Pregnancy and breastfeeding
- Active skin infection, inflammatory lesions or open wounds in the treatment area
- Hernia in the planned area, particularly for abdominal applications
- Bleeding disorders, or anticoagulant use that has not been reviewed
- Uncontrolled metabolic, autoimmune or connective tissue disease
- Pacemakers, defibrillators, metal implants or intrauterine devices — relevant for energy-based and electromagnetic methods
- Severe cold-related conditions such as cryoglobulinaemia, where cooling-based methods are concerned
- Known allergy to the material planned for injection-based methods
- Expectations of a surgical-level change
Please share your full medication list and medical history before a plan is made, including supplements, recent weight change and any procedure carried out elsewhere in the past year.
When do results become visible?
The timeline follows the mechanism. Methods that damage fat cells depend on the body clearing them, which is a gradual process: a change is typically noticed from around the fourth week and continues to develop for two to three months after the session. Nothing meaningful is visible in the first days.
Microinjection methods work over a course rather than a single visit; changes in surface texture and circulation are usually assessed after several sessions rather than immediately. Muscle stimulation follows a different curve again — the effect builds across the course and, like any training response, is maintained with periodic sessions.
The endpoint of a plan is therefore reviewed at a set interval after the final session, not on the day it ends. Measurements taken before starting make that review more reliable than memory.
Combining applications
Combination is the rule rather than the exception in this category, because the layers being addressed are different. Reducing a fat deposit does nothing for the muscle beneath it, and improving muscle tone does not change the surface texture of the skin above. A plan that pairs a fat-focused method with muscle stimulation, or adds a microinjection course for surface irregularity, is addressing separate problems rather than doubling up on one.
Sessions are spaced deliberately rather than stacked. Appropriate intervals between energy-based, cooling-based and injection-based applications are set during planning, and the response to the first stage usually informs what follows.